Warung Bebas
Tampilkan postingan dengan label healthcare IT deaths. Tampilkan semua postingan

Senin, 16 September 2013

An Open Letter to David Bates, MD, Chair, ONC FDASIA Health IT Policy Committee on Recommendations Against Premarket Testing and Validation of Health IT

From http://www.healthit.gov/policy-researchers-implementers/federal-advisory-committees-facas/fdasia:

The Food and Drug Administration Safety Innovation Act (FDASIA) Health IT Policy Committee Workgroup is charged with providing expert input on issues and concepts identified by the Food and Drug Administration (FDA), Office of the National Coordinator for Health IT (ONC), and the Federal Communications Commission (FCC) to inform the development of a report on an appropriate, risk-based regulatory framework pertaining to health information technology including mobile medical applications that promotes innovation, protects patient safety, and avoids regulatory duplication.

My Open Letter to the Committee's chair speaks for itself:

From: Scot Silverstein
Date: Mon, Sep 16, 2013 at 9:39 AM
Subject: ONC FDASIA Health IT Policy Committee's recommendations on Premarket Surveillance
To: David Bates

Sept. 16, 2013

David Bates, Chair, ONC FDASIA Health IT Policy Committee
via email
   
Dear David,

I am disappointed (and in fact appalled) at the ONC FDASIA Health IT Policy Committee's recommendations that health IT including typical commercial EHR/CPOE systems not be subjected to a premarket testing and validation process.  I believe this recommendation is, quite frankly, negligent. [1]

As you know, my own mother was injured and then died as a result of EHR deficiencies, and nearly injured or killed again in the recuperation period from her initial injuries by more health IT problems in a second EHR used in her care.  In my legal consulting and from my colleagues, as well as from the literature, I hear about other injuries/deaths and many "near misses" as well.  That your recommendations came in the face of the recent ECRI Deep Dive study is even more appalling, with the latter's finding of 171 health IT-related incidents in 9 weeks from 36 member PSO hospitals, resulting in 8 injuries and 3 possible deaths, all reported voluntarily. [2]

It is my expert opinion the issues that cause these outcomes would never have made it into production systems, had a reasonable, competent, unbiased premarket testing and validation process been in place.

Consequently, I have shared the FDASIA HIT Policy Committee's recommendations with the Plaintiff's Bar, and will use its recommendations in my presentations to various chapters of the American Association for Justice (the trial lawyer's association) - as well as to interested Defense attorneys so they may advise their clients accordingly.

I am also making recommendations that in any torts, individual or class, regarding EHR problems that would likely have been averted with competent premarket testing and validation, that the FDASIA HIT Policy Committee members who agreed with the recommendation be considered possible defendants.

I am sorry it has come to this.

Please note I am also posting this message for public viewing at the Healthcare Renewal weblog of the Foundation for Integrity and Responsibility in Medicine (FIRM).

Sincerely,

Scot Silverstein, MD
Consultant/Independent Expert Witness in Healthcare Informatics
Adjunct Faculty, Drexel University, College of Computing and Informatics

Notes:


[1] FDA Law Blog, Recommendations of FDASIA Health IT Workgroup Accepted, September 11, 2013, available at http://www.fdalawblog.net/fda_law_blog_hyman_phelps/2013/09/recommendations-of-fdasia-health-it-workgroup-accepted.html: "Of particular interest is the recommendation that health IT should generally not be subject to FDA premarket requirements, with a few exceptions:  medical device accessories, high-risk clinical decision support, and higher risk software use cases."

[2] "Peering Underneath the Iceberg's Water Level: AMNews on the New ECRI 'Deep Dive' Study of Health IT Events" , Feb. 28. 2013, available at http://hcrenewal.blogspot.com/2013/02/peering-underneath-icebergs-water-level.html.

-----------------------------------------------

Note: the following are listed on the linked site above as members of the committee:

Member List
  • David Bates, Chair, Brigham and Women’s Hospital
  • Patricia Brennan, University of Wisconsin-Madison
  • Geoff Clapp, Better
  • Todd Cooper, Breakthrough Solutions Foundry, Inc.
  • Meghan Dierks, Harvard Medical Faculty, Division of Clinical Informatics
  • Esther Dyson, EDventure Holdings
  • Richard Eaton, Medical Imaging & Technology Alliance
  • Anura Fernando, Underwriters Laboratories
  • Lauren Fifield, Practice Fusion, Inc.
  • Michael Flis, Roche Diagnostics
  • Elisabeth George, Philips Healthcare
  • Julian Goldman, Massachusetts General Hospital/ Partners Healthcare
  • T. Drew Hickerson, Happtique, Inc.
  • Jeffrey Jacques, Aetna
  • Robert Jarrin, Qualcomm Incorporated
  • Mo Kaushal, Aberdare Ventures/National Venture Capital Association
  • Keith Larsen, Intermountain Health
  • Mary Anne Leach, Children’s Hospital Colorado
  • Meg Marshall, Cerner Corporation
  • Mary Mastenbrook, Consumer
  • Jackie McCarthy, CTIA - The Wireless Association
  • Anna McCollister-Slipp, Galileo Analytics
  • Jonathan Potter, Application Developers Alliance
  • Jared Quoyeser, Intel Corporation
  • Martin Sepulveda, IBM
  • Joseph Smith, West Health
  • Paul Tang, Palo Alto Medical Foundation
  • Bradley Thompson, Epstein Becker Green, P.C
  • Michael Swiernik, MobileHealthRx, Inc.
Federal Ex Officios
  • Jodi Daniel, ONC
  • Bakul Patel, FDA
  • Matthew Quinn, FCC

 -- SS

Jumat, 13 Juli 2012

Did Toxic Effects of an EHR Kill Rory Staunton?

A stunning story about the death of a young man from sepsis (blood poisoning by infection), missed in an ED, appeared in the New York Times:

An Infection, Unnoticed, Turns Unstoppable

By JIM DWYER
New York Times
Published: July 11, 2012

For a moment, an emergency room doctor stepped away from the scrum of people working on Rory Staunton, 12, and spoke to his parents.

“Your son is seriously ill,” the doctor said.

“How seriously?” Rory’s mother, Orlaith Staunton, asked.

The doctor paused.

“Gravely ill,” he said.

How could that be?

Two days earlier, diving for a basketball at his school gym, Rory had cut his arm. He arrived at his pediatrician’s office the next day, Thursday, March 29, vomiting, feverish and with pain in his leg. He was sent to the emergency room at NYU Langone Medical Center. The doctors agreed: He was suffering from an upset stomach and dehydration. He was given fluids, told to take Tylenol, and sent home.

Partially camouflaged by ordinary childhood woes, Rory’s condition was, in fact, already dire. Bacteria had gotten into his blood, probably through the cut on his arm. He was sliding into a septic crisis, an avalanche of immune responses to infection from which he would not escape. On April 1, three nights after he was sent home from the emergency room, he died in the intensive care unit. The cause was severe septic shock brought on by the infection, hospital records say. 

Rory Staunton, age 12, 5 feet 9 inches tall and 169 pounds, had suffered a cut on his arm.  He presented with a marked fever of 102 F (39 C), pulse markedly elevated at 131, respiratory rate elevated at 22; reported to have hit as high as 36 breaths per minute (in essence, panting).  It was reported by the NYT that before the ED visit his parents said his temperature had reached 104 F (40 C).

That alone should have set off some level of concern.  (It is possible narrative details of his history never made it into the ED chart; ED EHR's are often templated point-and-click affairs that can impair or discourage capture of narrative.)

Per the NYT, the bacteria Streptococcus pyogenes normally dwells in the throat or on the skin, areas where the body is well defended.  Also known as Group A streptococcus, the strain typically causes strep throat or impetigo.  However, if it gets into the blood stream (e.g., via a cut in the skin, as this patient suffered playing ball), the results can be devastating.

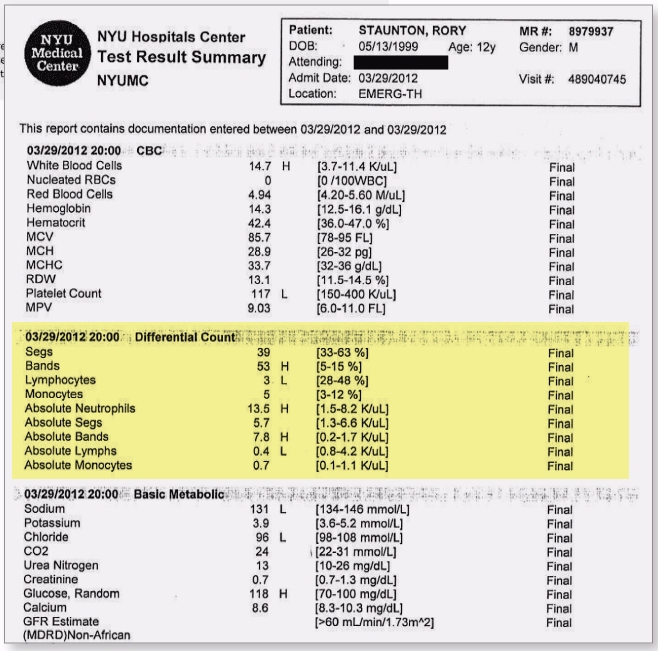
The lab results from the first ED visit are particularly stunning:


(From NYT article; click to enlarge)


The white blood cell count is markedly elevated at 14.7, meaning 14,700 cells per microliter of blood (cubic millimeter or 1 mm3).  Further, there is a plain evidence of greatly accelerated new white cell production, in the form of "bands", at 53% of the total (normally 5-15%).  Bands are immature white blood cells that are seen in the blood, being produced as part of the body's response to infection.

Herein is a significant issue.  The NYT noted that:

"Three hours later [i.e., after the ED visit, which reportedly only lasted 2 hours - ed.], Rory’s blood tests came back. High levels of neutrophils and “bands” – immature white blood cells – are evidence of infection. But nobody called the Stauntons, and by the time Rory returned to the hospital the next day, his infection was unstoppable. He died two days later."

Not getting into the issue regarding the patient apparently being discharged before the labs got back (itself an invitation to disaster), and the other abnormalities such as low sodium, low platelets, elevated glucose all pointing to a very sick patient... nobody called the Stantons with white cell results like these?   Nobody entertained the thought of ... antibiotics as a precaution?

It is possible - dare I say likely - that no clinical person in the ED ever saw these results.

EHR's that are poorly designed or implemented can have a toxic effect on care.  For instance, EHR's can cause user confusion if the user interface is complex, data can be lost due to poor relational design.  Data from the wrong patient's data can be presented (misidentification), or data from a lab can come back to the system after a patient has left, and despite being abnormal, just sit there in a silo without being looked at ("out of sight, out of mind"; a "silent silo" syndrome).

It is usually difficult to ascertain exactly which EHR product is being used at a particular hospital.  I note this medical center actively promoted its EPIC EHR in a June 2011 press release "NYU Langone Medical Center Launches Next Phase of Its Electronic Health Record System", although another system "ICIS"  (for Integrated Clinical Information System, "a state-of-the-art healthcare information management system that connects all NYULMC caregivers involved in patient care") is mentioned here.  The ICIS may also contain the Eclipsys Sunrise Clinical Manager, per this link. (I'd noted some clinically relevant problems with the latter in an FDA report here.)

In any case, magical powers are attributed to the technology that are not strongly or uniformly supported by the literature (link), but strongly pushed by industry marketing memes of deterministic health IT benefits and absolute beneficence:

“... Our electronic health record system is an integral part of our ongoing efforts to leverage technology and enhance our ability to provide patient-centered care and enable the highest level of quality care management,” said Bernard A. Birnbaum, MD, senior vice president and vice dean, chief of hospital operations at NYU Langone. “These front-end and back-end services are an important step in assuring our patient’s experience from beginning to end is a seamless one.”

I've documented examples of situations where EHR's and other IT components of clinical ERP systems (enterprise resource planning and management systems, a term that more accurately describes what exists in many hospitals now than the misleading, file cabinet-evoking term "EHR") contributed to or caused patient harm, such as at "Babies' deaths spotlight safety risks linked to computerized systems" - a computer error caused a central line placement x-ray to have gone unread, leading to death; "The Sweet death that wasn't very sweet" - a missing "difficult intubation" EHR flag led to a middle-aged man suffocating during an intubation attempt; and others.  An Australian researcher thoroughly studied the potential risks of an EHR meant specifically for ED's ("A Study of an Enterprise Health information System", PDF executive summary at this link).

The following passage in the NYT article also offers another clue:

... Two hours later, though, he had three [signs of sepsis]: his temperature had risen to 102, his pulse was 131 and his respiration rate was 22. But by the time those vital signs were recorded, at 9:26 p.m., they had no bearing on his treatment. In fact, the doctor had already decided that Rory was going home. Rory’s “ExitCare” instructions, signed by his father, were printed 12 minutes before those readings. 

Did those readings escape notice due to delayed charting (data entry), a common problem with EHRs in busy clinical environments?

The Institute of Medicine in its 2011 IOM report on health IT safety admitted harms are reported but the magnitude of harms is unknown due to multiple reporting impediments, as did the FDA in its 2010 internal memo on "H-IT Safety Issues" divulged by the Huffington Post Investigative Fund (see here and here).  The National Institute of Standards and Technology (NIST) admits in its 2011 report on HIT usability that EHR usability is often poor and may lead to "use error" (error caused or promoted by poor design, as distinguished from simple user error, see here), magnitude of problem also unknown.

In a startling medical situation such as Rory Stanton's, where crucial labs seem to have evaporated causing or contributing to delayed treatment of a devastating and obvious illness, I believe EHR-related factors need to be examined and ruled out first.

For, quite simply, if the EHR caused or contributed to this tragic debacle, the public could be at risk.


-- SS

Additional thought:  could this be the "cybernetic Libby Zion case" I've written of?

-- SS

July 18, 2012 Addendum:

The Stauntons, who appeared on the NBC Today Show are seeking to create a “Rory’s Law” in New York to ensure that parents have full access to blood and lab tests done on their children as soon as results are available, and that a doctor will be present to assess the findings. Story here.

-- SS

Sabtu, 31 Maret 2012

An Expensive Healthcare Computing Mistake: $1.5 Million

At my June 2011 post "Babies' deaths spotlight safety risks linked to computerized systems" I reported on a case (case #2) of an infant death in part attributed to HIT (PACS) interference in otherwise simple care processes.

In "Allen-Blake vs. Abington Memorial Hospital", a critical x-ray of a PICC (peripherally inserted central catheter) line placement allegedly was never read due to misdating.

The Allen-Blake case was settled 2/29/12 for $1.5 million, according to the public docket count 78 (link):

2/29/2012OrderOF 2/28/12 OTT, J PROPOSED SETTLEMENT OF $1,500,000.00 APPROVED CC

That $1.5 million might have paid for a lot of other things, such as provision of better medical care through hiring/retention of more staff. The legal fees for defense incurred must also have been substantial, representing yet more precious healthcare capital down the proverbial drain.

Add cases like this to the "total cost of ownership" of health IT.

-- SS
 

ZOOM UNIK::UNIK DAN UNIK Copyright © 2012 Fast Loading -- Powered by Blogger